
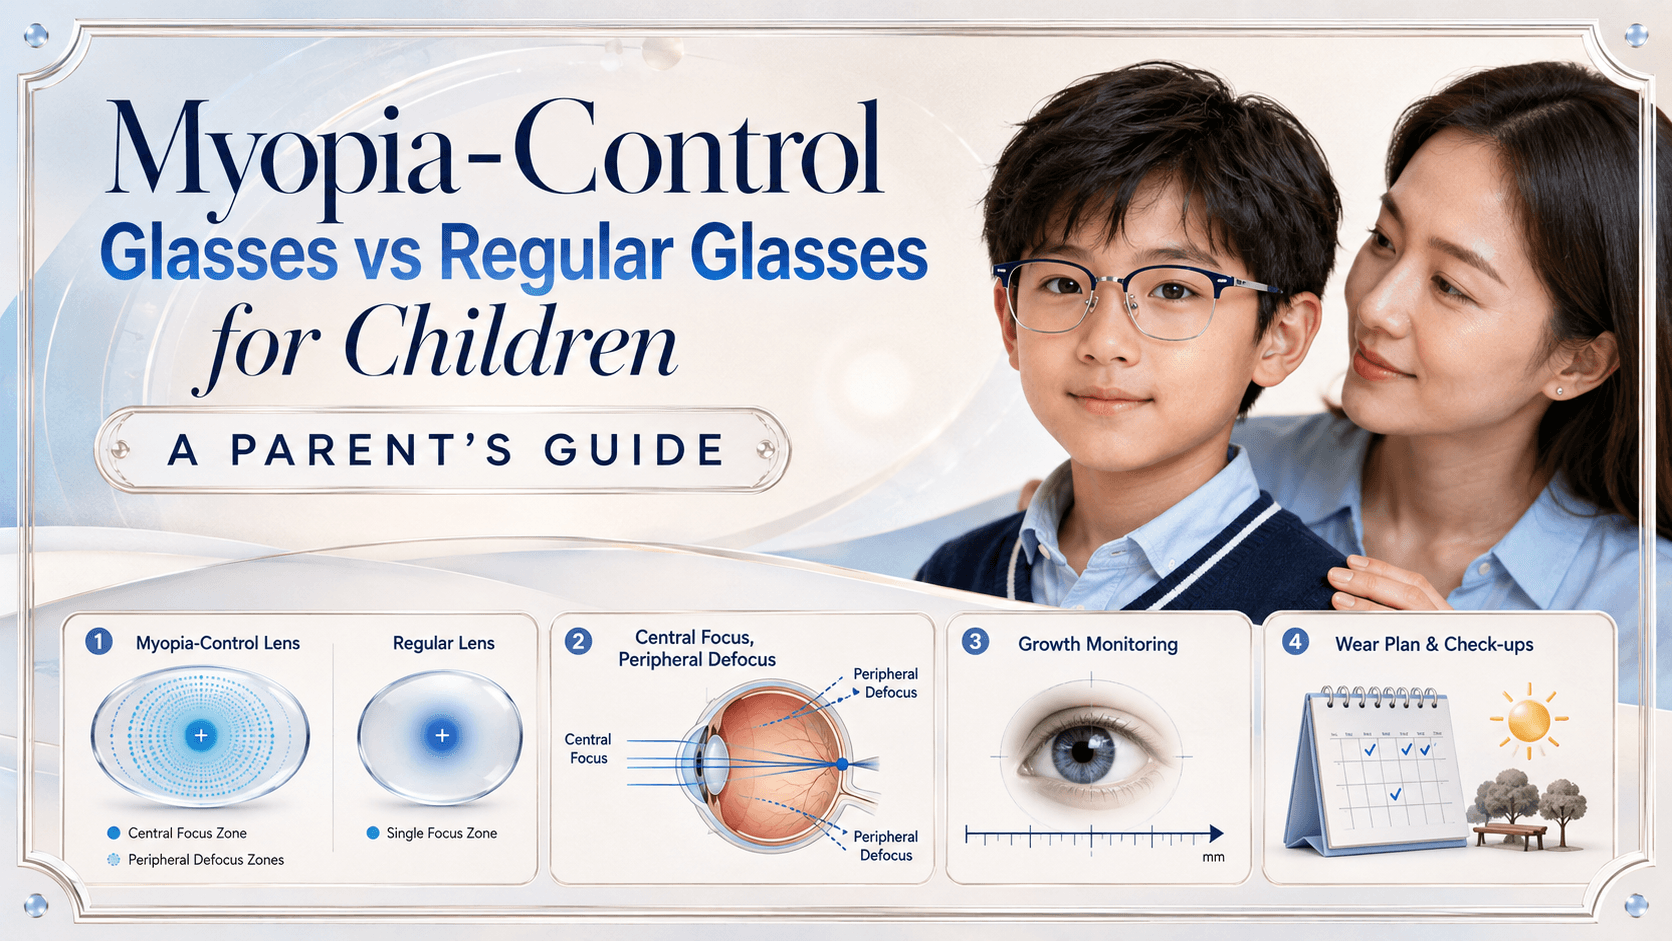
Myopia-control glasses are specially designed lenses that slow the progression of short-sightedness in children, whereas regular prescription glasses simply correct the blur without influencing how the eye grows. If your child's myopia is worsening by more than 0.50D per year, an eye specialist may recommend myopia-control lenses as an active intervention rather than passive correction.
What Is Myopia Progression and Why Does It Matter?
Myopia (short-sightedness) in children is not just a vision problem — it is a structural change in the eye. As the eyeball elongates faster than it should, the prescription keeps climbing. High myopia (above -6.00D) significantly raises the lifetime risk of retinal detachment, glaucoma, and macular degeneration. Slowing progression during childhood, when the eye is still growing, can make a meaningful difference to your child's long-term eye health.
How Do Myopia-Control Glasses Work?
Standard single-vision lenses correct central vision but leave peripheral defocus in a way that may signal the eye to keep elongating. Myopia-control lenses — such as DIMS (Defocus Incorporated Multiple Segments) and HALT (Highly Aspherical Lenslet Target) designs — use a zone of peripheral lenslets to create a competing signal that tells the eye to slow its growth. Clinical studies show these lens designs can reduce myopia progression by 50–60% on average compared with standard single-vision lenses.
Myopia-Control Glasses vs Regular Glasses: Key Differences
Purpose: Regular glasses correct existing blur; myopia-control glasses correct blur and actively work to slow further worsening.
Lens design: Standard lenses have a uniform prescription; myopia-control lenses have a central correction zone surrounded by peripheral lenslets or aspherical zones.
Cost: Myopia-control lenses typically cost more than standard single-vision lenses due to advanced optical engineering.
Adaptation: Some children need 1–2 weeks to adapt to the lenslet pattern, though most adjust without difficulty.
Effectiveness window: These lenses work best between ages 6 and 16, when the eye is most actively growing.
When Should You Choose Myopia-Control Glasses?
Discuss myopia-control lenses with your child's ophthalmologist or optometrist if: the prescription has increased by 0.50D or more in the past year; one or both parents are highly myopic; or your child spends significant time on screens and limited time outdoors. Regular glasses remain appropriate for children with stable, low myopia or for those whose specialist confirms slow progression.
Practical Tips for Parents
Ensure your child wears the glasses for the recommended hours each day — consistent wear is critical for the lenslet-based signal to work. Schedule eye exams every six months rather than annually so progression can be tracked accurately. Encourage at least 90 minutes of outdoor time daily, which research consistently links to slower myopia progression regardless of the lens type used.
When you are ready to explore options, look for lenses with published clinical data behind them. Ask your eye care professional for the axial length measurement at each visit — this is a more precise indicator of eye growth than prescription change alone.
